One of the most mechanically complex and clinically important areas of the human body sits at the top of the spine, where the head meets the neck. This region, called the cranial cervical junction (CCJ), is where your skull connects to your uppermost vertebrae: C1, C2, and C3.

A network of strong ligaments holds this structure together, including the supraspinous and interspinous (SS/IS) ligaments and the nuchal ligament. These connective tissues do more than keep your head up. They hold the uppermost spinal segments in place, help protect the delicate neural structures that run through the region, and keep the brain and spinal cord aligned.
With age, trauma, repetitive strain, or disease, these ligaments can become weakened, stretched, or damaged, and the consequences reach beyond simple neck pain.
CCJ instability occurs when the ligaments that hold the cranio-cervical junction (the junction between the skull and upper cervical spine) become lax or damaged, allowing the joints in this area to move beyond their normal range.
This extra mobility, known as hypermobility, can set off a chain of problems. The joints are exposed to abnormal stress, which can drive degenerative change and arthritis. Muscles compensate for the lost ligament support and become chronically strained and painful. Nerves passing through the area can be compressed or overstretched, and connective tissue is repeatedly loaded beyond its designed tolerance.
The result is a set of symptoms that can be difficult to diagnose and trace back to a single cause, because the CCJ sits at the crossroads of several systems: skeletal, muscular, and neurological.
Symptoms of CCJ instability may include:


For a long time the muscles and ligaments of the neck were taught as separate from the dura mater, the tough membrane that surrounds the brain and spinal cord. Anatomical research over the past few decades has changed that picture. Since 1995, studies have mapped a dense network of connective tissue called the myodural bridge, which links the deep suboccipital muscles to the dura.
More recent dissection and plastination work has described additional structures, including the vertebral dura ligament (VDL) and a “to-be-named” ligament, that connect the upper cervical spine to the dura. The rectus capitis posterior minor (RCPmin) muscle, a small but important muscle between C1 and the base of the skull, attaches to the dura through this bridge.
These are not anatomical footnotes. They point to a real mechanical and neurological relationship between the neck and the membranes around the brain and spinal cord.
Why the dura matters: the dural sac encloses the cerebrospinal fluid (CSF) that bathes the brain and spinal cord. CSF cushions the nervous system, helps clear waste, and supports a stable internal environment. The dura is also supplied by pain-sensitive nerve fibers, so physical strain or distortion of the dura can directly produce pain.
If the upper neck muscles and ligaments attach to the dura, then movement and strain in the neck can be transmitted to the dura itself. This has practical implications for how CCJ instability is understood, diagnosed, and treated.
Because the dura carries pain-sensitive nerves, mechanical pull from the neck may stimulate that nerve supply, which researchers have proposed as one contributor to headaches that do not fit a standard pattern. This is one hypothesis offered for why some patients with CCJ instability report recurrent headaches, cognitive symptoms, and other complaints that routine exams do not explain.
In plain English: your neck may be pulling on the protective covering of your brain, and that pull is one possible source of headaches and neurological-type symptoms that have been hard to account for. This mechanism is plausible and supported by anatomy, but it is still an area of active research rather than settled fact.

Direct mechanical links between the cervical spine and the dura matter for any surgical approach to the CCJ. Procedures in this region, including stabilization, decompression, and fusion, interact with the dura and potentially with CSF dynamics.
Surgery can change the shape and tension of the dural tube, and changes in dural shape may affect CSF flow. In some cases surgical intervention makes the CCJ more stable. In others it may alter dural mechanics in ways that affect symptoms. The available evidence on diagnosis and surgical outcomes in this area is still limited.
None of this means surgery is never appropriate. In severe CCJ instability, surgical stabilization (such as occipitocervical fixation) can be clinically indicated, and a subset of patients with connective-tissue disorders genuinely require it. It does mean the decision deserves careful, individualized consideration, and that non-surgical options are usually worth exploring first.
If surgery has been recommended for CCJ or upper cervical instability, it is reasonable to ask your specialist how the procedure accounts for dural mechanics and CSF flow, and to seek a second opinion from a clinician experienced in this region before proceeding.
The same anatomy that complicates surgery also strengthens the rationale for targeted rehabilitation. If there is a continuous line of mechanical structures from the neck to the dura, then improving the mechanics of the neck may also reduce abnormal load on the dura.
A considered non-surgical program for CCJ instability can include several elements:


Many people with CCJ instability look entirely well from the outside. Blood tests come back normal. Standard MRI may be normal. Yet daily life can be genuinely disabling.

The symptoms are real, the mechanisms are better understood than before, and help is available. The first and most important step is an accurate diagnosis from a clinician who knows this region well.
Conditions at the junction of the cervical spine and the nervous system call for more than a general musculoskeletal skill set. They require detailed knowledge of the anatomy, the mechanical relationships described in the research, and the right diagnostic and therapeutic tools.
Our NYDNRehab head and neck specialists treat CCJ instability with:


Several factors can contribute, including traumatic injury (whiplash, falls, direct impact to the head or neck), postural stress over time, inflammatory conditions, and connective tissue disorders such as Ehlers-Danlos syndrome (a condition where connective tissue is abnormally lax). In some patients, no specific cause is identified.
Diagnosis relies on a thorough clinical examination, history, and appropriate imaging. Instability may not show clearly on standard MRI or X-ray, so specialized imaging, including upright MRI, dynamic flexion-extension X-rays, and digital motion X-ray (DMX), may be used. Diagnostic criteria remain an area of debate among specialists, which is one reason it is important to be assessed by a clinician familiar with this region.
It may. Because the upper cervical muscles and ligaments connect mechanically to the dura, CCJ instability can stretch the dura and stimulate its pain-sensitive nerve supply, which may produce headaches. These are often described as cervicogenic headaches (headaches arising from the neck) and may not respond to standard migraine treatment.
They are related but not identical. Atlantoaxial instability refers specifically to instability of the C1-C2 joint (the atlas and axis). CCJ instability is a broader term covering instability of the whole cranial cervical junction (occiput-C1 and C1-C2), either alone or in combination.
For many patients, yes. Non-surgical rehabilitation, when delivered by clinicians experienced in this region and tailored to the specific mechanical and neurological picture, can provide meaningful and lasting improvement. How far conservative care can go depends on the severity of the instability, the structures involved, and the individual presentation.
If you have persistent neck pain, unexplained or poorly treated headaches, neurological symptoms, or some combination of these, CCJ instability may be an overlooked contributing factor.
The specialists at NYDNRehab have the knowledge, diagnostic tools, and treatment options to evaluate your situation accurately and build a plan based on current clinical evidence and your individual needs.
Call NYDNRehab’s head and neck specialists to schedule a consultation. The sooner an accurate diagnosis and rehabilitation plan are in place, the better your chances of a real recovery, and the lower the risk of unnecessary or premature surgery.

Request an appointment»

Our location: 11 West 25th Street 5th floor, New York, NY 10010
Dr. Lev Kalika is a world-recognized expert in musculoskeletal medicine. with 20+ years of clinical experience in diagnostic musculoskeletal ultrasonography, rehabilitative sports medicine and conservative orthopedics. In addition to operating his clinical practice in Manhattan, he regularly publishes peer-reviewed research on ultrasound-guided therapies and procedures. He serves as a peer reviewer for Springer Nature.
Dr. Kalika is an esteemed member of multiple professional organizations, including:

Below is a prime example of how ultrasound can take the guesswork out of diagnosis.

A bad physical therapy experience is one of the primary causes of unnecessary surgery

In this instance, an athlete was originally diagnosed with minor quadriceps muscle strain and was treated for four weeks, with unsatisfactory results. When he came to our clinic, the muscle was not healing, and the patients’ muscle tissue had already begun to atrophy.
Upon examination using MSUS, we discovered that he had a full muscle thickness tear that had been overlooked by his previous provider. To mitigate damage and promote healing, surgery should have been performed immediately after the injury occurred. Because of misdiagnosis and inappropriate treatment, the patient now has permanent damage that cannot be corrected.
The most important advantage of Ultrasound over MRI imaging is its ability to zero in on the symptomatic region and obtain imaging, with active participation and feedback from the patient. Using dynamic MSUS, we can see what happens when patients contract their muscles, something that cannot be done with MRI. From a diagnostic perspective, this interaction is invaluable.
Dynamic ultrasonography examination demonstrating
the full thickness tear and already occurring muscle atrophy
due to misdiagnosis and not referring the patient
to proper diagnostic workup
Demonstration of how very small muscle defect is made and revealed
to be a complete tear with muscle contraction
under diagnostic sonography (not possible with MRI)
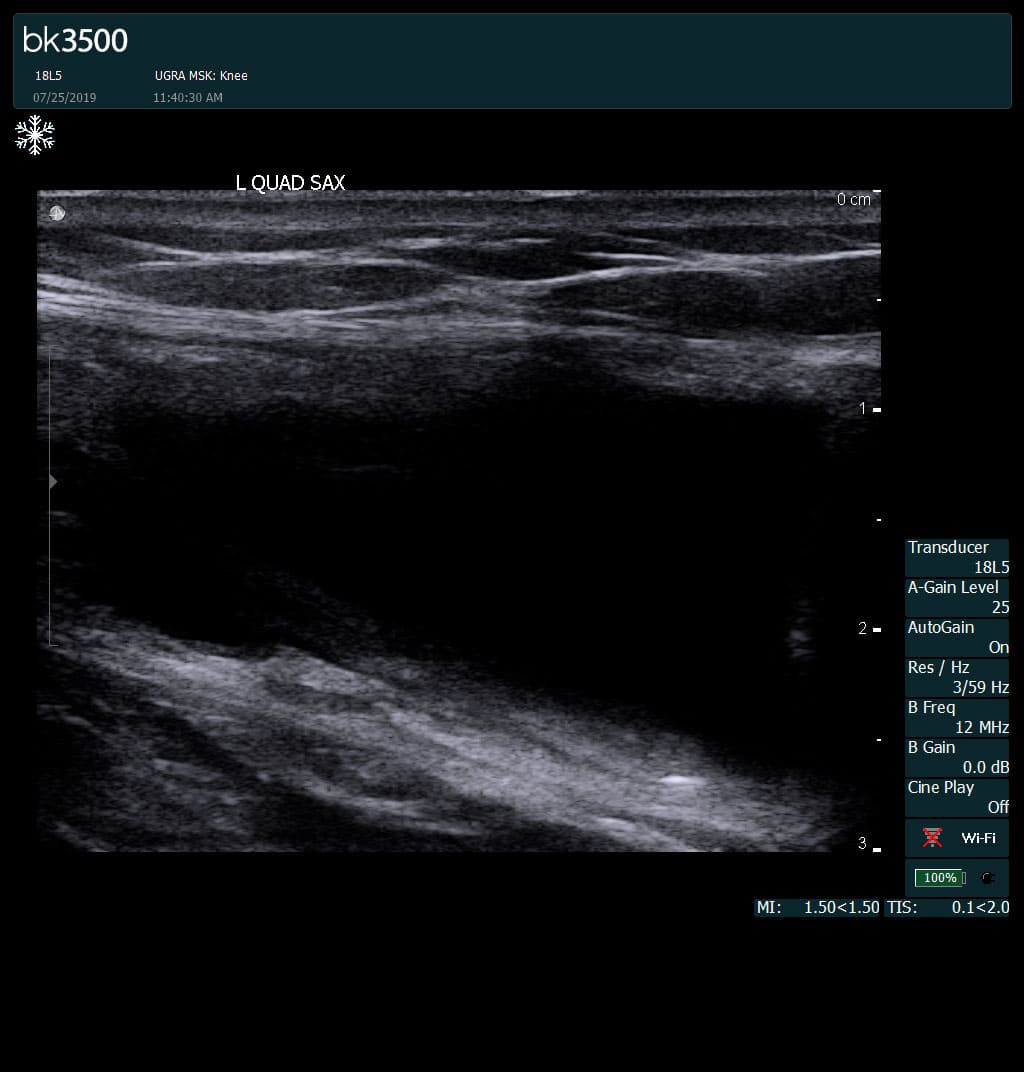
Complete tear of rectus femoris
with large hematoma (blood)
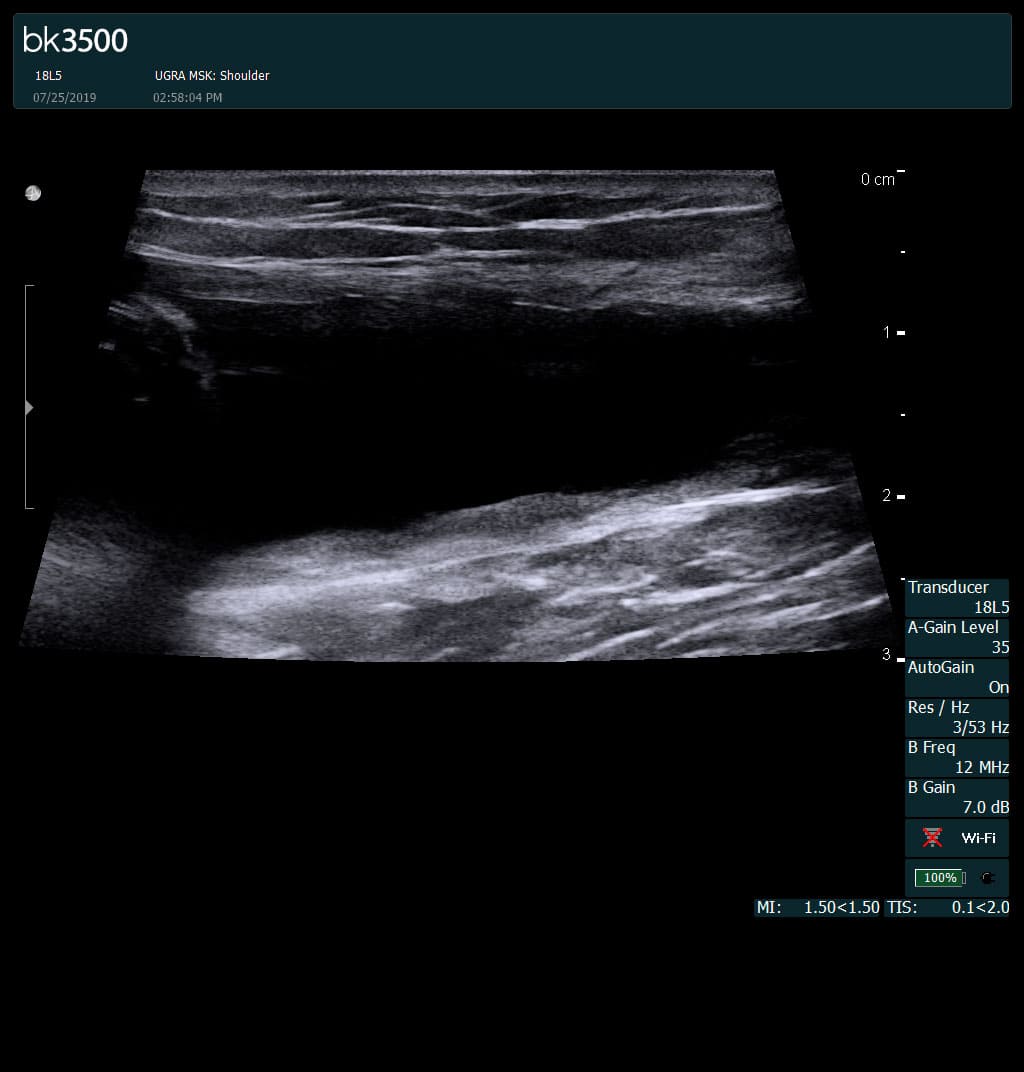
Separation of muscle ends due to tear elicited
on dynamic sonography examination


 Request Telehealth