Request Telehealth
Dry Needling for Frozen Shoulder Syndrome
Personalized boutique services supported by cutting-edge
integrative diagnostics and advanced holistic therapies.
Integrative Shoulder Specialists Kalika and
Brosgol

Clinical director & DC RMSK
Verified Expert Profiles


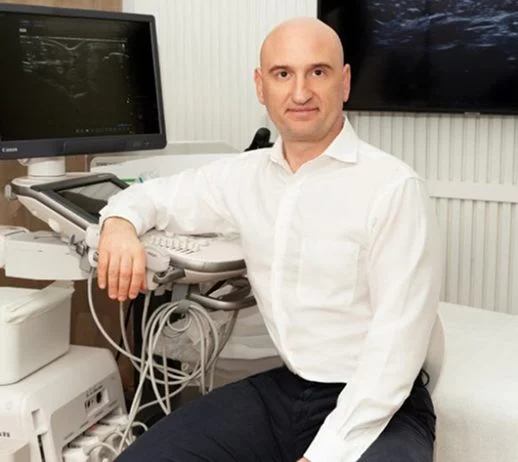
Dr. Lev Kalika, DC, RMSK, clinical director of NYDNRehab, has a successful track record of providing advanced holistic approaches that bring superior results to patients suffering from pain syndromes and movement disorders. Dr. Kalika has 20+ years of hands-on clinical experience in diagnostic ultrasonography, and is an esteemed member of the American Institute of Ultrasound in Medicine (AIUM).
In addition to operating his clinical practice in Manhattan, Dr. Kalika regularly publishes and presents peer-reviewed research on ultrasound-guided procedures, including dry needling and shockwave therapy. Dr. Kalika’s unique approach has helped numerous frozen shoulder patients to quickly restore pain-free shoulder function, without drugs or surgery.

Dr. Yuri Brosgol, MD, is a neurologist with 25+ years of experience in treating myofascial ,orthopedic and chronic pain conditions. Working together with Dr. Kalika, Dr. Brosgol performs ultrasound-guided injection procedures to treat frozen shoulder cases with precision, for optimal results.
Together, Dr. Kalika and Dr. Brosgol are revolutionizing the way frozen shoulder syndrome is diagnosed and treated by leveraging the most advanced technologies and therapies currently available.
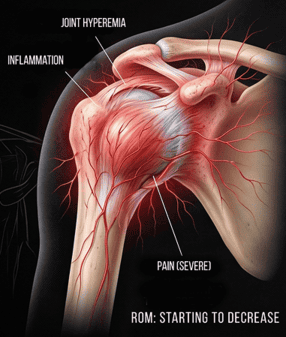
The most painful stage where pain gradually worsens and range of motion starts to decrease. This stage often lasts from 6 weeks to 9 months.
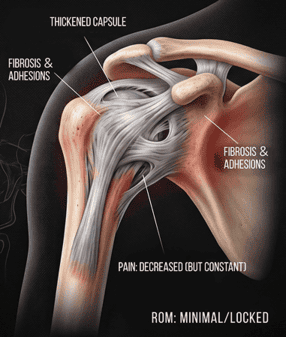
Pain decreases slightly, but stiffness increases, interfering with daily activities. The frozen stage can last between 4-12 months.
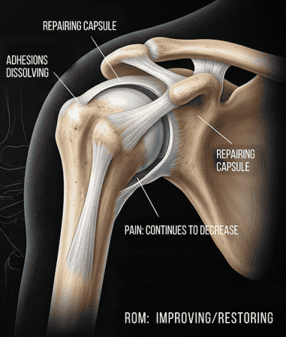
Range of motion slowly improves as pain continues to decrease. This phase can take from 5 months to 2 years or more.
While the specific causes of adhesive capsulitis remain unclear, we know that lack of physical activity can contribute to and worsen frozen shoulder symptoms. Prolonged immobilization after an injury or surgery is often a factor.

Adhesive capsulitis symptoms include:
- Dull, achy pain in the outer shoulder area, sometimes radiating to the upper arm.
- Shoulder stiffness and limited range of motion, making it difficult to move the shoulder.
- Pain that worsens with movement, especially in the early stages
- Pain that intensifies at night, causing sleep disruptions.
- Difficulty reaching overhead or behind your back, or lifting your arm.
Key risk factors include:
- Type 2 diabetes (highest prevalence)
- Poor posture
- Thyroid problems
- Female sex
- Middle age (40-60)
- Chronic systemic inflammation
- Sedentary lifestyle
- Metabolic disorders
Advanced Diagnostic Tools Mean Better Treatment
Doctors typically rely on the patient’s health history, reported symptoms, and clinical exam results to diagnose frozen shoulder syndrome, but that approach does not always reveal the source and scope of the condition.
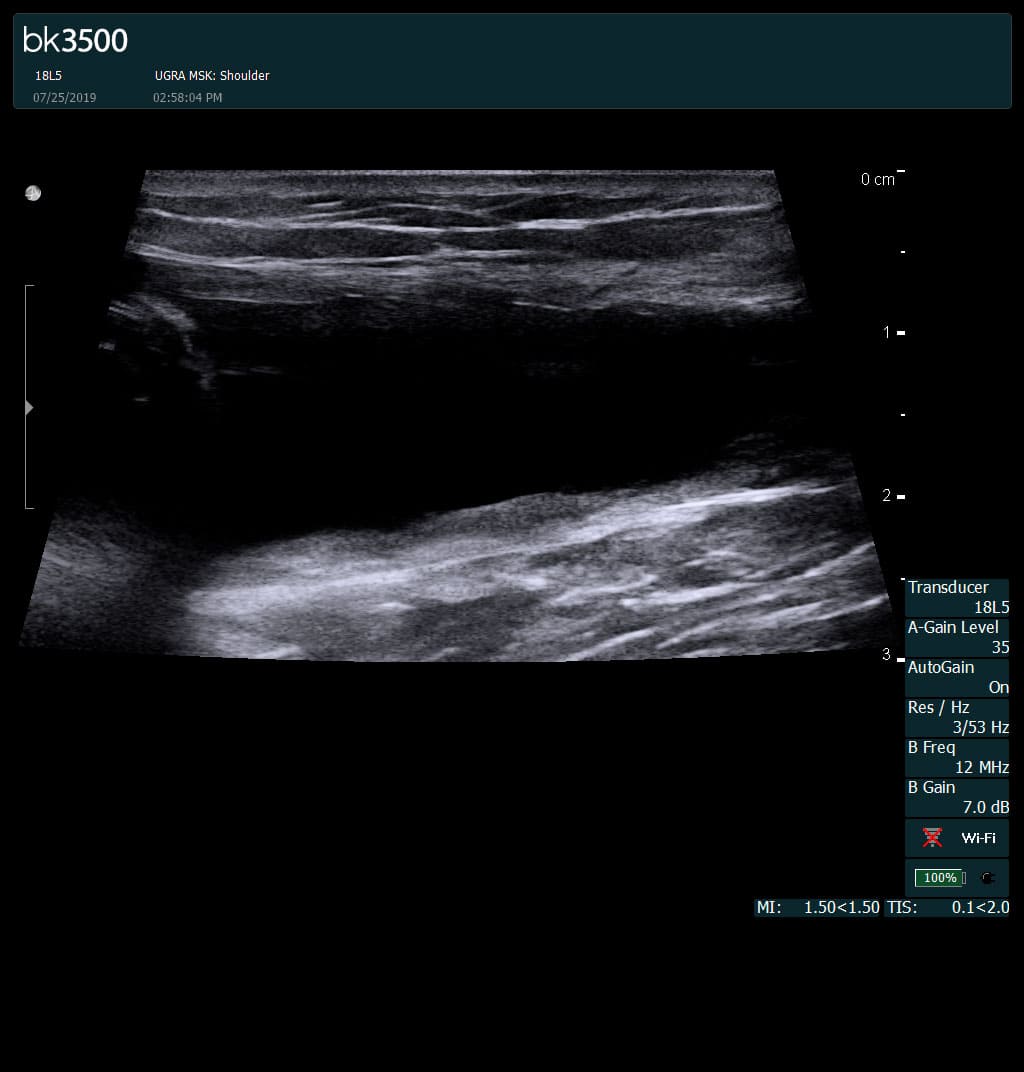
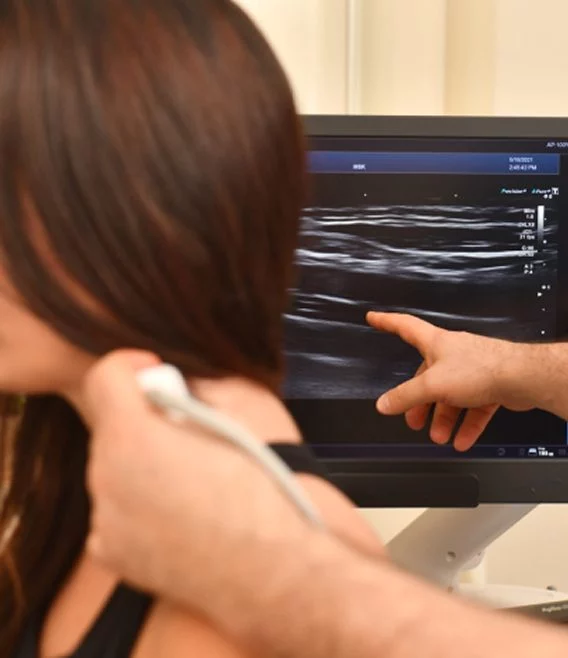
At NYDNRehab, we use high-resolution diagnostic ultrasound to visualize the myofascial structures surrounding and affecting the shoulder joint.
Ultrasound enables us to:
- Compare the affected and unaffected shoulders.
- Identify densified fascial layers and trigger points.
- Visualize nerves entrapped by fascial adhesions that intensify pain.
- Examine the shoulder in motion, in real time.
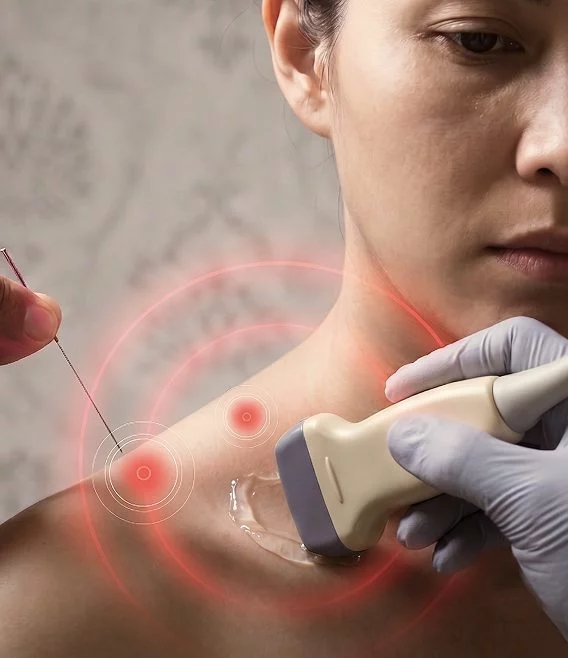
Ultrasound equips us to detect deep tissue trigger points in hard-to-reach places like the pelvic floor, deep spinal muscles, muscles affecting the temporomandibular joint (TMJ), thoracic muscles, and more. The ability to visualize the dry needling procedure in real time ensures that deep tissue trigger points are accurately targeted while protecting neurovascular bodies and vital organs from needle penetration.
Dr. Kalika has spent years developing his skills in ultrasonography and interpreting its results. His in-depth grasp of human anatomy and myofascial dynamics, and his extensive research on ultrasound guided procedures is recognized by his peers at the American Institute of Ultrasound in Medicine (AIUM).
At NYDNRehab, frozen shoulder patients receive a comprehensive ultrasound exam on the first visit, in the comfort of our clinic. Thorough and accurate diagnosis puts you on the fast track toward resolving your shoulder pain and restoring functional shoulder range of motion.
How Dry Needling Fits Into Frozen Shoulder Treatment at NYDNRehab
For true adhesive capsulitis, current evidence supports dry needling as an adjunct, not as a primary treatment. A 2021 pre/post study of shoulder-girdle trigger point needling combined with conventional physiotherapy showed significant short-term gains in pain, range of motion, disability, and pressure pain threshold, but the design had no control group, so the contribution of needling alone cannot be isolated. A separate randomized trial in shoulder adhesive capsulitis comparing intramuscular electrical stimulation with plain dry needling, both added to therapeutic exercise, found needling-based neuromuscular treatment effective for pain, disability, trigger points, and abduction and external rotation range of motion. The major clinical practice guideline for adhesive capsulitis still centers treatment on irritability-based education, pain control, joint mobilization, stretching, and exercise, with dry needling positioned as a supportive intervention rather than a core one.
At NYDNRehab, we use this evidence to position dry needling where it does the most work: addressing myofascial trigger points and pain-mediated movement restriction associated with adhesive capsulitis. The clinically honest framing is that dry needling is a supportive treatment, not a primary one. It is not the right option for moderate to severe frozen shoulder, where the capsular contracture and the inflammatory irritability dominate the picture. It is a good supporting modality in the thawing phase, and in cases of mild frozen shoulder, where pain and irritability are lower and the myofascial component is doing a larger share of the work. We then combine it with the therapies that act directly on the capsule and on shoulder mechanics. Recovery timelines vary by stage and by underlying biology, particularly in diabetic frozen shoulder where the fibrotic process is more aggressive, but pairing needling with capsular and mechanical work tends to give faster symptom relief than waiting the condition out alone.
The therapies below make up our integrated frozen shoulder program. Each one targets a specific driver of the condition, with dry needling layered in where it adds the most value.
When Dry Needling Helps Most in Frozen Shoulder
Dry needling does the most work when part of the shoulder restriction is driven by myofascial trigger points, protective muscle spasm, pain inhibition, or secondary scapulothoracic and rotator cuff guarding. In those situations, releasing the muscular component lets the rest of the rehab program (capsular mobilization, graded stretching, scapular control work) take effect faster. In cases dominated by a stiff, fibrotic capsule with a hard end feel, needling alone will not unlock the joint, and the primary work has to be capsular.
Dry needling is most useful when:
- You are in the thawing phase, where pain and irritability have settled and the dominant restriction is muscular rather than capsular.
- You have a mild presentation of frozen shoulder, with manageable pain and only moderate loss of range of motion, where dry needling can serve as a useful adjunctive modality alongside stretching and mobilization.
- Trigger points in the subscapularis, latissimus or teres major, pec minor, upper trapezius, levator scapulae, or posterior rotator cuff are limiting external rotation and elevation.
- The shoulder behaves like a “pseudo-frozen” shoulder, where passive range of motion improves quickly after soft tissue or fascial work, suggesting the restriction is not yet capsular.
- The frozen shoulder developed secondary to rotator cuff tendinopathy, post-surgical or post-injury immobilization, or cervical and scapular guarding patterns.
Dry needling on its own is less effective when:
- The frozen shoulder is moderate to severe, where capsular contracture and high tissue irritability dominate and dry needling is not the right primary option.
- The shoulder shows a true capsular pattern with a hard, blocky end feel on passive motion.
- The frozen shoulder is diabetic in origin, where the underlying fibrotic biology is more aggressive and tends to resist soft tissue work alone.
- The frozen stage has been long-standing and the capsule has marked structural contracture.
- Glenohumeral accessory motion is globally restricted and external rotation is severely blocked, which points to a capsular rather than a myofascial driver.
In these scenarios, dry needling can still help reduce pain and protective tone, but the heavy lifting comes from capsular mobilization, graded stretching, ultrasound-guided hydrodilatation or steroid injection, and, depending on irritability, shockwave or EMTT for pain modulation. The clinical exam at your first visit is what determines which mix is right for your shoulder.


Frozen Shoulder Dry Needling FAQs
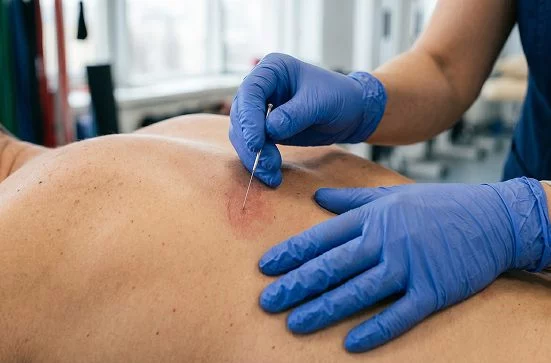
Dry needling is an evidence-based technique where thin, non-medicated (dry) needles are inserted into myofascial trigger points to release tension, reduce pain, and improve blood flow. For frozen shoulder syndrome, it targets muscles around the shoulder (like the upper trapezius, infraspinatus, deltoid, subscapularis, levator scapulae, and rotator cuff) that often develop tightness or trigger points. Dry needling can help to decrease pain, relax muscles, and increase shoulder range of motion.
The dry needling procedure may cause sensations of pressure or cramping, often from a local twitch response in the muscle). Needle insertion is quick, and any discomfort is brief. You may feel post-treatment soreness similar to a workout, usually lasting 24–48 hours.
The number of sessions varies by severity, the stage of progression, and individual factors. For some, 1-2 sessions is enough to reduce symptoms, while others may need more. Dry needling is most effective when combined with other treatment approaches and physical therapy.
Dry needling offers multiple benefits for adhesive capsulitis treatment, including:
- Fast pain relief.
- Improved shoulder range of motion.
- Enhanced effects of other therapies.
- Accelerated recovery.
Many clinicians encourage gentle movement or light exercise immediately after a dry needling session to enhance the procedure’s effects. However, you should avoid heavy lifting or aggressive stretching on the same day as your dry needling session.