Request Telehealth
SHOULDER BLADE & INTERSCAPULAR PAIN
Personalized boutique services supported by cutting-edge integrative diagnostics and advanced holistic therapies.
Still Suffering from Undiagnosed Shoulder Blade Pain?
If you’ve seen multiple providers without a clear answer, you’re not alone. Pain around and between the shoulder blades is one of the most misdiagnosed complaints in sports and regenerative medicine and standard imaging is usually why.
The scapula is the largest bone in the shoulder complex, with 17 muscles attached to it. Some of those tendon-aponeurosis attachments are so small they can only be visualized with ultrasound. The nerve path from the neck to the shoulder blade is equally complex, passing through the brachial plexus. Because of their minute size, injuries to these tendons and nerves routinely go undiagnosed and undertreated.

STEP 1: FULL HISTORY & CLINICAL EXAM Before any imaging, we build a complete picture: where your pain started and how it has changed, which movements make it better or worse, and what treatments you have already tried and why they may not have worked. A failed treatment isn’t a dead end. It’s a diagnostic clue.
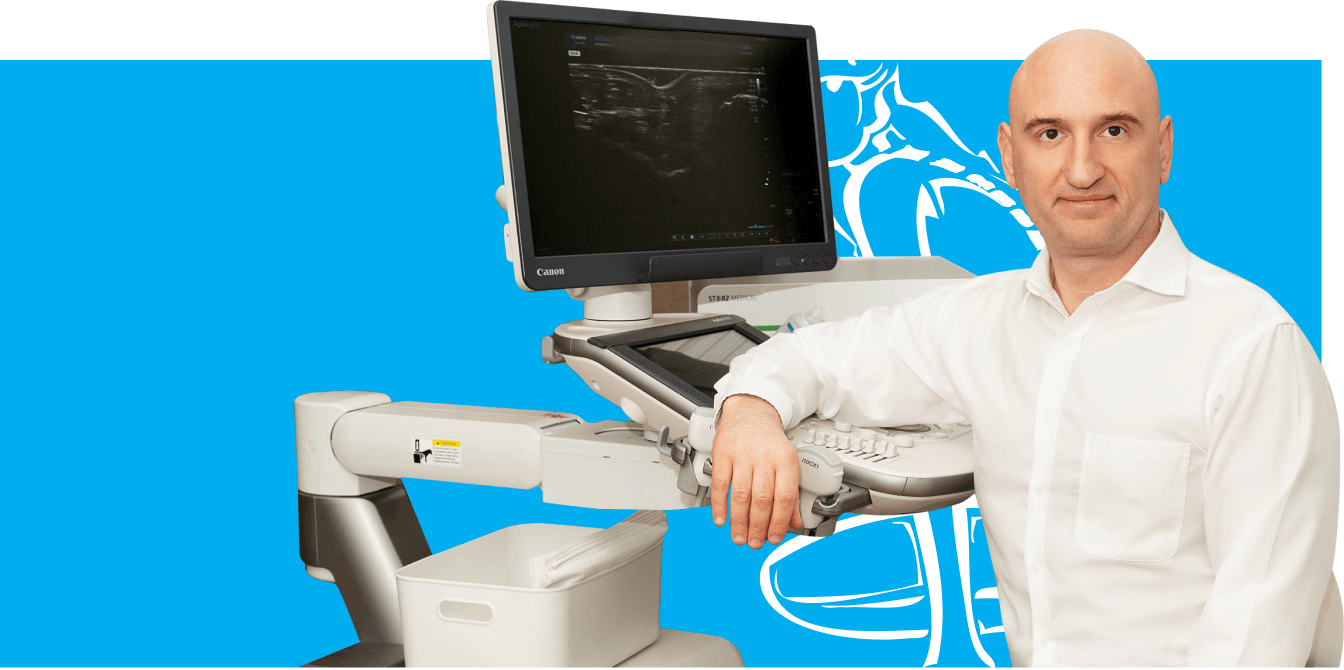
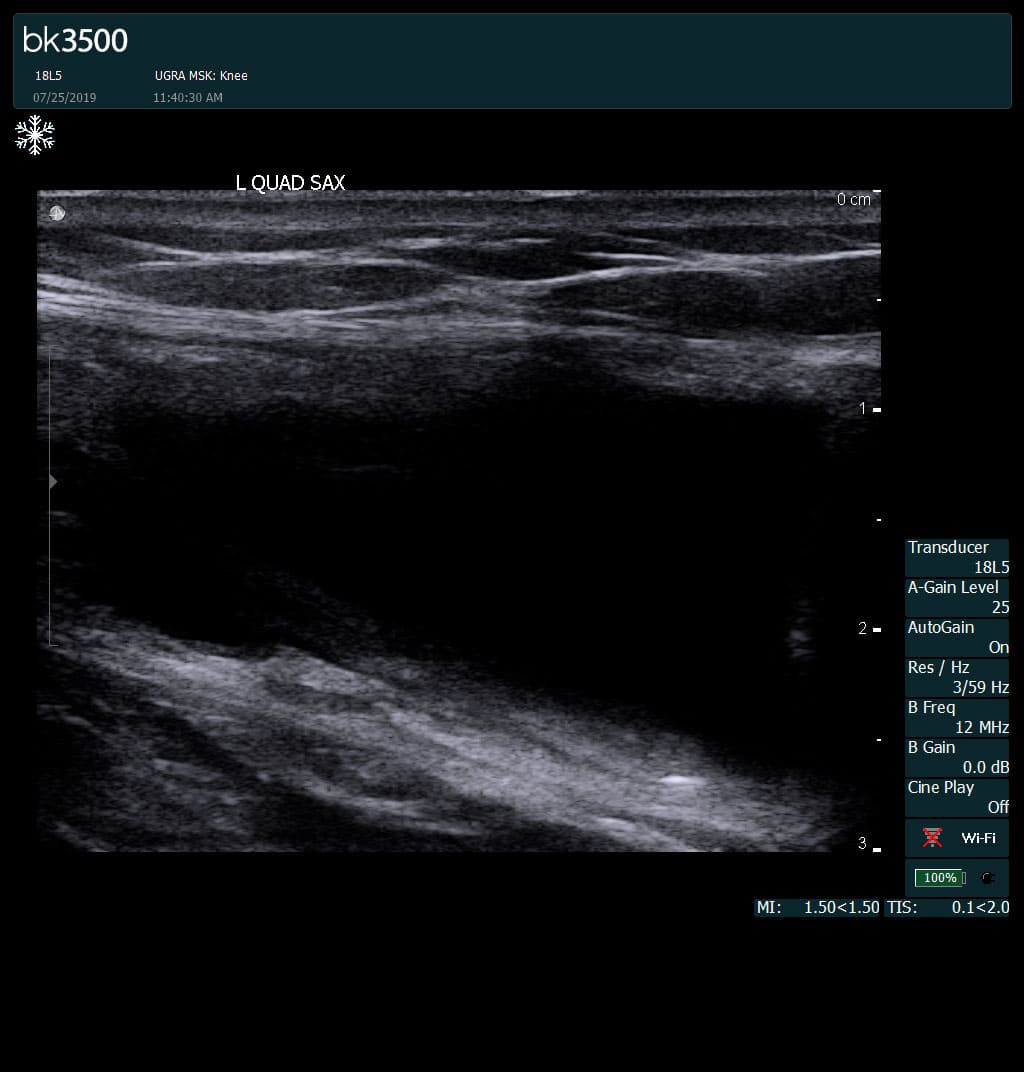
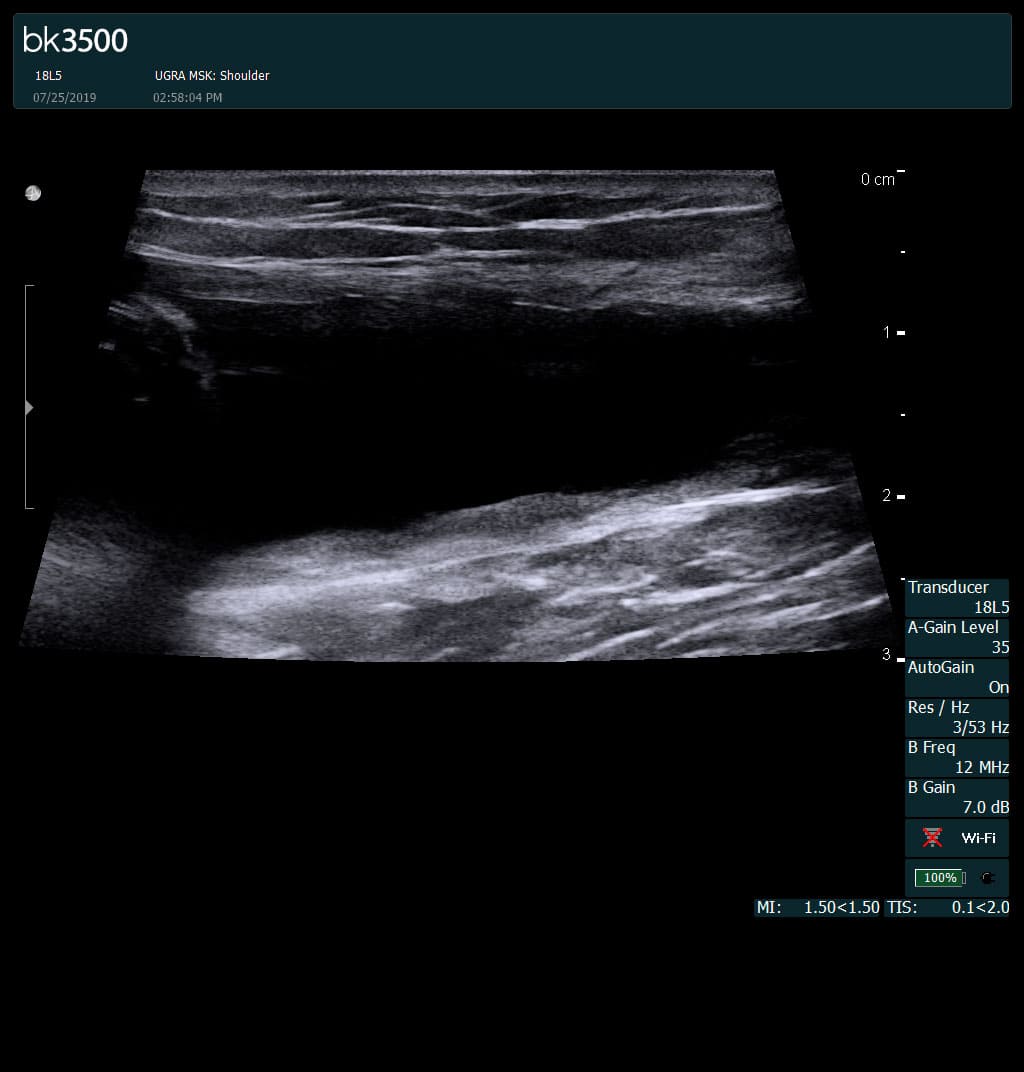
STEP 2: DYNAMIC SCAPULAR ULTRASOUND Unlike an MRI, ultrasound lets us see your shoulder blade while it moves. We track nerves along their full path, identify micro-tears in muscle attachments, and observe how tendons and fascia glide or fail to glide under load, during the exact movements that provoke your pain.
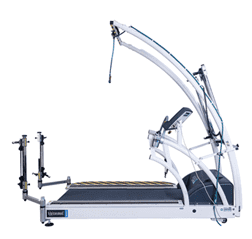
STEP 3: 3D KINEMATIC ASSESSMENT For patients who haven’t responded to conventional care, this is often the missing piece. Our 3D kinematic assessment measures how your scapula, shoulder, spine, and rib cage move together, simultaneously, under real load. It does not simply show whether the scapula moves abnormally. It helps determine why.
STEP 4: TARGETED TREATMENT REHABILITATION Once we identify the underlying drivers, we build a treatment protocol around your specific mechanics not a generic plan. Restored mobility is then maintained through progressive, targeted loading, and we continuously test and reassess throughout your care to ensure the protocol progresses appropriately.
Our Clinical Philosophy
- Dr. Lev Kalika
Rather than viewing shoulder blade pain as a diagnosis, we view it as the visible result of an underlying mechanical problem. The scapula is designed to move, freely, precisely, and in coordination with the neck, ribs, spine, and shoulder. When that movement is disrupted, pain is often the first signal that something within the larger system has broken down.
Our goal is not simply to treat the painful shoulder blade. It is to understand why the scapula stopped moving normally in the first place, so that recovery is not only achieved, but maintained.

Dr. Lev Kalika


 Verified Expert
Dr. Lev Kalika is an internationally recognized expert on the role of the scapula in shoulder pathology. He studied directly under Dr. Ben Kibler, the orthopedic surgeon who pioneered the clinical understanding of scapular dyskinesis.
Over more than two decades he has built a clinical approach dedicated specifically to disorders of the shoulder blade and scapulothoracic complex. High-resolution dynamic ultrasonography allows him to clearly visualize the peripheral scapular nerves, tendon-aponeurosis attachments, myofascial trigger points, and fascial ruptures and adhesions, a methodology that requires both top-of-the-line equipment and extensive operator experience.
He is one of few practitioners in the United States specializing in scapular diagnostic ultrasonography, is a certified practitioner of Stecco Fascial Manipulation, and lectures internationally on scapular imaging and ultrasound-guided rehabilitation.
recognized expert
in scapular disorders

Symptoms and Causes of Shoulder Blade Pain
Why Is It So Hard to Diagnose?
Your shoulder blade connects to your neck, ribs, spine, and shoulder all at once. Pain can come from any of these areas — or several at the same time.

Nerve, muscle, and joint problems feel the same without real-time testing

Your neck, spine, or ribs may be the true source

Standard MRIs often can't detect compressed nerves in motion

Static tests miss dysfunctions that only appear when you move
Shoulder Blade Pain Is More Than a Shoulder Problem
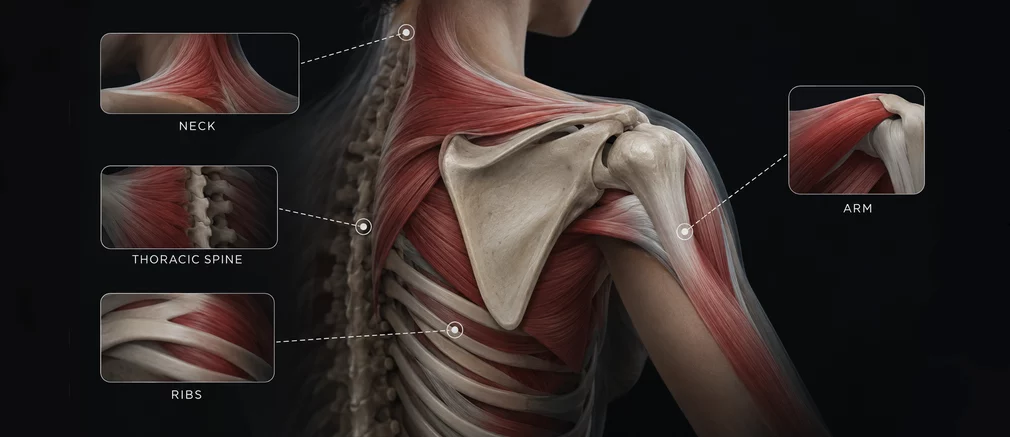
One of the most common misconceptions about shoulder blade pain is that the problem begins and ends at the scapula. In reality, the shoulder blade functions as a central link between the neck, shoulder, rib cage, thoracic spine, and upper extremity. Even small disturbances anywhere within this interconnected system can alter how the blade moves and where pain is felt.
Research by our own clinical team has framed the scapula as a mechanical hub in human movement, associated not only with shoulder disorders but with dysfunction across connected regions:
- Cervical spine, neck dysfunction frequently refers pain directly to the blade
- Thoracic spine & ribs, stiffness here alters how the blade glides and rotates
- Elbow & hand, scapular dysfunction can influence force transmission down the arm
- Headaches, altered scapular mechanics have been linked to tension-type headache

Can refer significant pain to the blade with no neck symptoms at all

Directly influence how the blade glides, yet are rarely examined

Seldom tested on standard imaging, despite driving persistent pain
Scapular Conditions We Diagnose
and Treat
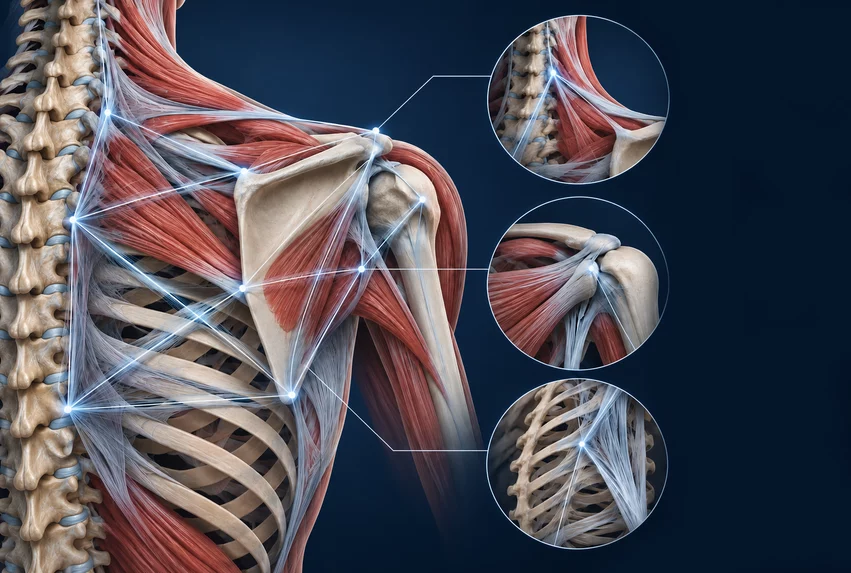
The Scapula Is Part of an Entire
Tensegrity System
Modern biomechanics increasingly recognizes that the shoulder blade functions within an interconnected network of muscles, fascia, ligaments, ribs, and the spine rather than as an isolated bone.
This concept aligns with the principles of biotensegrity, an influential framework first described by orthopedic surgeon Dr. Stephen Levin and expanded through modern fascia research. It is best understood as a clinically useful lens rather than an established fact, and it complements current biomechanical and fascial research on why shoulder blade pain so often resists treatment directed at a single structure.
Building on advanced training in fascial science with Carla Stecco, Dr. Lev Kalika has developed a clinical application of these principles to dynamic musculoskeletal ultrasonography. His approach extends beyond identifying isolated tissue abnormalities to evaluating how fascial continuity, tissue gliding, force transmission, and movement patterns interact during functional motion, allowing dynamic ultrasound to reveal biomechanical dysfunctions that may not be apparent on conventional static imaging.



Why Previous Physical Therapy
May Have Failed
Most conventional practitioners zero in on posture as the main cause of shoulder blade pain. While posture is a likely factor, once there is pain and dysfunction in the scapula, postural correction and conventional physical therapy is not usually sufficient to correct the condition.
If you have been going to therapy for weeks or months and you still don’t feel better, it is not because you are not doing your work. Many patients undergo a long scapular strengthening program to no avail since muscle weakness may not have been the main issue.

The neck may be driving blade dysfunction, not the blade itself

Restricted gliding can prevent normal movement from returning

Strengthening around a compressed nerve reinforces the painful pattern

Altered rib mechanics change how the blade moves, yet are rarely assessed

Exercises may target the compensation, not the original cause

Loading before mobility and inflammation are addressed causes setbacks

Small aponeurotic tears are invisible without high-resolution imaging

Subtle joint laxity keeps reloading the same painful pattern
When the underlying mechanical problem goes unrecognized, strengthening alone can reinforce abnormal movement patterns rather than correcting them.

A failed course of physical therapy is diagnostic information. It tells us what was overlooked, and points us toward the real solution.
— Dr. Lev Kalika
The NYDNRehab Scapular Diagnostic Model





The first-step bridge that connects your symptoms, movement history and clinical findings to a functional map that guides all imaging and treatment decisions.
See our complete shoulder diagnostic model for glenohumeral, rotator cuff, and labral pathology.
Dynamic Scapular Ultrasound
The diagnosis of scapular pathology is usually based on the history and physical examination and testing of strength and range of motion. This can help rule out the causes and may miss important details of your injury, leading to improper care, chronic pain and unnecessary health care expenses.
Unlike an MRI, ultrasound allows us to observe your shoulder blade as it moves:
- Nerves along their full path, to find where compression occurs
- Muscle attachments that may not show up on MRI, but can cause micro-tears and lesions
- The way tendons and fascia move, or don’t move, when loaded
- Scars, thickening and adhesion of the fascial layers
- The specific motion and/or location that causes the pain
- An actual comparison of the painful and normal sides

3D Upper Body Kinematic Assessment
This is the key element that is missing for patients who have failed to respond to traditional treatment. We have a 3D kinematic assessment which measures the movement of your scapula, shoulder, spine and rib cage together simultaneously (under real load).
What we measure:
- Scapular rotation, tilt and glide on rib cage
- Left vs. right, to find the exact location of the painful side
- The distinction between primary and secondary dyskinesis, motor control or compensation
- The entire kinetic chain (neck to ribs to shoulder)
Movement analysis doesn’t just reveal if the scapula is moving abnormally, it also helps to uncover the reason for that. When used in conjunction with dynamic ultrasound, it helps differentiate between pain inhibition, muscle dysfunction, cervical issues, nerve injury, instability, fascial restriction, and compensation from other areas of the body that are causing altered movement.
Fascial Gliding Assessment
The healthy layers of tissue slide easily over each other. After injury, overloading, surgery or chronic inflammation, these interfaces can become restricted, densified or adhered, slightly changing the scapular motion, irritating nerves and causing chronic pain. These changes are often not seen in conventional static imaging.
Based on the principles of Stecco Fascial Manipulation®, we evaluate:
- When there is limited motion at the shoulder girdle and thoracic wall
- Changes in the blade motion due to densifications and adhesions
- Tender points that refer into interscapular region
- Whether restriction is local or part of a broader compensation chain
Peripheral Nerve Ultrasound
Dorsal scapular, spinal accessory, long thoracic and intercostal nerves may all cause pain patterns similar to those of muscular or joint problems. These nerves are small and dynamic entrapment is very common, so they are rarely detected on routine static imaging. With high resolution ultrasound we can follow each nerve from its point of origin, through the brachial plexus and out to the scapular area and reproduce the compression in real motion.
Why This Combination Changes Everything
Standard Approach
- Static MRI snapshot
- Isolated shoulder examination
- Treat the symptom
- Trial and error
NYDNRehab Approach

movement


Shoulder Blade Treatment Options
After we determine the root causes of your pain and movement dysfunction, we develop a treatment plan that is unique to your mechanics, not a generic plan. Restoring motion in the muscles and joints is not enough for effective rehabilitation, sometimes it is necessary to restore motion between the layers of the connective tissue that allow the muscles and joints to move freely. As research into fascial manipulation continues, it is best used in a comprehensive, personalized treatment plan.
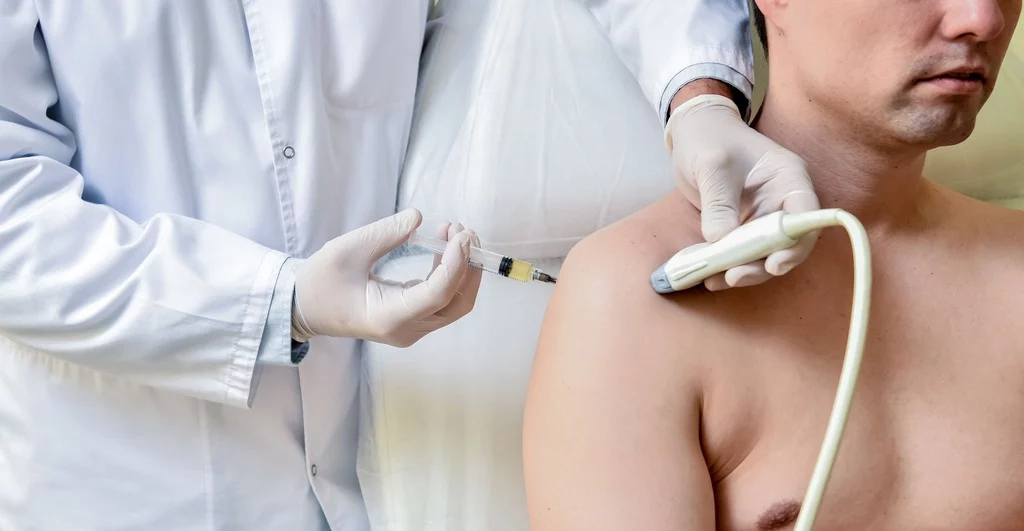
Hydrodissection
Restores normal gliding between restricted tissue layers
Targets densification altering shoulder girdle mechanics
Promotes structural healing where tissue injury is present

Maintains restored mobility through progressive, targeted loading
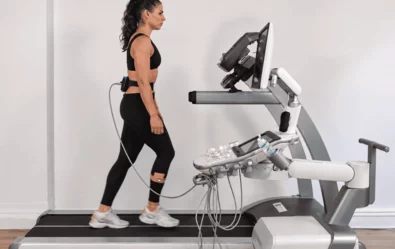
Correcting dynamic control using objective kinematic data

Evaluating how past injuries and posture feed current pain
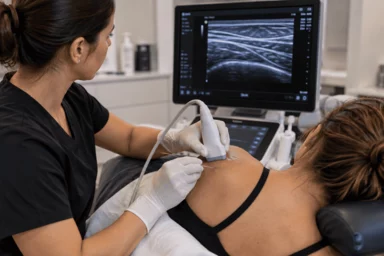
Releasing deep myofascial trigger points with imaging precision
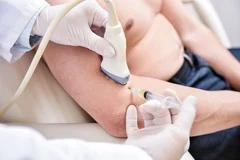
Supporting structural tissue repair

Stimulating the body's natural healing response

Restoring developmental movement strategies

Restoring nerve mobility along the neck-to-scapula pathway
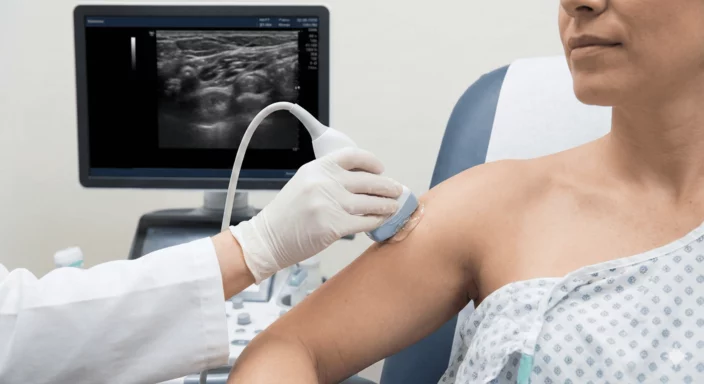
Testing throughout care to keep the protocol progressing
Restoring Fascial Glide and Tissue Mobility
Successful rehabilitation often requires restoring normal motion not only within muscles and joints but also between the connective tissue layers that allow those structures to move freely.
Drawing from the principles of Stecco Fascial Manipulation®, we assess areas where fascial densification may restrict normal force transmission and alter movement patterns throughout the shoulder girdle.

("FLUSH" injections) to restore normal tissue glide

techniques targeting densified fascial centers

when structural tissue injury is present

designed to maintain restored tissue mobility
Regenerative Therapies for Scapular Pain
When structural damage to tendons, fascia, nerves, or muscles contributes to persistent pain, physical therapy alone may not be sufficient. Regenerative therapies activate the body’s own repair mechanisms, a process similar to the cascade the body uses to heal any injured tissue.

- Low-energy acoustic waves delivered via a hand-held transducer
- Non-invasive, requires no anesthesia
- Stimulates tissue repair and promotes microvascular regeneration
- Studied specifically in snapping scapula and shoulder tendinopathy

- Pulsed electromagnetic fields delivered externally to targeted tissues
- Supports cellular repair and reduces local inflammation
- Comfortable, non-invasive, and well tolerated
- Combined with ESWT, may help accelerate tissue recovery
What Recovery Looks Like
Recovery timelines depend on the structural cause, how long you have had symptoms, and your individual tissue healing rate.




Ready for Real Answers?
Stop guessing. Stop treating symptoms.
If you’ve been living with unresolved shoulder blade pain, the answer isn’t more of the same treatment, it’s a more complete diagnosis.
We use high-resolution diagnostic imaging and objective movement analysis to find the real driver of your scapular pain, and build treatment around what we actually find.
Our Awards






Clinical Case Studies
NYDNRehab
These case studies reflect real clinical conditions evaluated at NYDNRehab using advanced diagnostic methods and individualized rehabilitation strategies. All cases are evaluated and managed by Dr. Lev Kalika and the NYDNRehab clinical team.
Shoulder Blade Pain FAQs
Interscapular pain rarely starts between the blades. It usually comes from the thoracic spine and rib joints, from an irritated intercostal nerve, from myofascial trigger points in the deep layers of the mid-back, or from the neck referring pain downward. Prolonged desk posture is a common aggravator, but it is an aggravator rather than a cause, which is why posture correction alone so often fails to resolve it.
A normal MRI rules out major structural tears but cannot capture movement disorders, dynamic nerve entrapments, or fascial adhesions. Real-time ultrasound and movement analysis reveal what static imaging misses.
Yes. Cervical spine dysfunction frequently refers pain directly to the scapular region with no neck stiffness or discomfort whatsoever.
Pain returns when treatment targets symptoms or compensation patterns rather than the root cause such as an undetected nerve entrapment or subtle joint instability.
A nerve supplying the muscles along the inner border of your shoulder blade becomes compressed, producing persistent burning, aching, or localized weakness and is one of the most frequently missed causes of chronic shoulder blade pain.
Unlike static scans, high-resolution dynamic ultrasound allows us to view nerves, muscles, tendons, and fascial layers gliding in real time, during the exact movements that trigger your pain.
Yes. Fascia is the connective tissue network that links muscles, tendons, nerves, and joints throughout the body. Injury, repetitive overload, surgery, or chronic inflammation may reduce normal tissue gliding between these structures. Although research into fascial dysfunction continues to evolve, clinical studies support the role of fascial restrictions in pain, altered movement, and impaired function in selected musculoskeletal conditions.
Scapular dyskinesis refers to altered or abnormal movement of the shoulder blade. It can appear as winging, early elevation, or loss of smooth rotation during arm movement. It may result from nerve problems, muscle inhibition, joint dysfunction, fascial restriction, or compensation patterns, which is why identifying the underlying cause matters more than treating the movement pattern alone.
Not always. Many patients with persistent shoulder blade pain have no significant findings on MRI. Pain can result from nerve irritation, altered movement patterns, fascial restrictions, or referred pain from the neck or ribs, none of which are reliably captured on standard static imaging.
Certificates and Continuing Education























 Lev Kalika
 Rostyslav Bubnov
 Lev Kalika