July 16, 2026


Most people assume bad posture is just an appearance issue. The physical consequences can be more meaningful than that. When the head sits in front of the shoulders, it is called forward head posture (FHP), and the load on the cervical spine rises substantially the further the head moves forward. For people who spend long hours at a desk or on a phone, this is associated with chronic neck pain, tension headaches, and limited shoulder mobility.
Excessive rounding of the upper back (thoracic kyphosis) narrows the chest cavity and may affect how the lungs expand during breathing, potentially reducing lung capacity during activity. An excessive inward curve of the lower back (lumbar lordosis) loads the facet joints and may accelerate disc wear over time. A flat-back posture, where the normal lumbar curve is largely lost, places unusual strain on the back of the spine and tends to produce a constant fatigued feeling in the lower back rather than acute pain.
These deviations are present to varying degrees and rarely occur in isolation. Thoracic kyphosis is often accompanied by rounded shoulders, and FHP almost always comes with tightness in the upper trapezius and pectoral muscles. The patterns are linked by fascia (the connective-tissue web surrounding muscles and organs) and by the way the nervous system has learned to organize movement over years.


The pelvic floor is affected too. Sustained anterior pelvic tilt (the pelvis tipping forward) has been reported in the physiotherapy literature to be associated with reduced pelvic floor muscle activation, which matters for core stability and continence. Most people are surprised by that relationship.
The clinical difference between passive devices and active feedback tools is significant. Passive braces work in place of your muscles. Feedback devices prompt your muscles to do the work themselves.
Passive posture braces worn for long periods can reduce the demand placed on the postural muscles of the thoracic spine. Muscles that are not required to support the body tend to weaken over time, sometimes called disuse atrophy. The brace then becomes necessary to maintain the improvement it created.
Most postural deviations are not purely structural; they are also neuromuscular. The motor cortex (the part of the brain controlling voluntary movement) has, over years, learned to treat a given position as “neutral.” A brace does not retrain the motor cortex. It imposes a shape from the outside while the movement programming stays the same.
Adherence is another problem. People often stop wearing posture braces after a couple of weeks because they are uncomfortable or inconvenient. Without accompanying exercise or movement training, posture returns within days.
That said, braces are not useless. For post-fracture recovery and for older adults with osteoporosis (reduced bone density), rigid bracing can provide meaningful pain relief during the acute healing phase. There is much less evidence for long-term posture correction in otherwise healthy adults.

The research landscape has shifted in recent years, with a growing body of work in physical therapy and sports medicine pointing toward active treatment as superior to passive bracing for long-term postural results.
A systematic review and meta-analysis of exercise-based interventions for forward head posture found that targeted strengthening of the deep cervical flexors (the small muscles at the front of the neck) together with thoracic extension exercises produces measurable improvements in head-neck alignment, with stronger evidence for active exercise than for passive bracing.
In non-specific chronic low back pain, randomized trials and a Cochrane review show that motor control exercise (training the body to coordinate the deep spinal stabilizers) outperforms passive modalities and bracing alone for pain and function, although no single form of exercise has proven clearly superior to other active approaches.
Wearable biofeedback has a reasonable evidence base over the last decade. Vibrotactile (vibration-based) feedback from wearable sensors during a training period appears to improve postural habits. Whether those gains persist once the device is removed is still under study.
From the kyphosis literature, posterior-chain resistance training (back extensors, rhomboids, and rotator cuff) can reduce thoracic kyphosis in older adults in several trials, though results across studies are mixed. Where it works, bracing alone without exercise does not appear to produce the same skeletal change.
The posture rehabilitation field has changed significantly over the last five years, driven by motion capture, sensor technology, and a better understanding of motor learning.
AI posture analysis uses computer vision to assess posture from standard video or images. It makes initial screening faster and more accessible, and some systems detect postural deviations with accuracy approaching that of trained clinicians. These tools are increasingly used to set objective pre-treatment baselines and to track change over time.
Digital postural assessment goes further, combining static posture photos, dynamic movement video, force-plate data, and patient-reported symptoms into a composite picture that is far more informative than visual inspection alone.
Motion capture and computerized gait analysis let clinicians see how posture changes during movement rather than only in standing. The difference can be large: a person may look perfectly straight standing still yet show significant spinal rotation asymmetry when walking, visible only on motion analysis.
Breathing-based posture work addresses a mechanism traditional bracing ignores. Diaphragm dysfunction (the dome-shaped main breathing muscle beneath the lungs) alters intra-abdominal pressure and shifts load onto the superficial back muscles. Restoring diaphragmatic breathing mechanics can reduce lower-back muscle tension and support a neutral spine without any external device.
Motor learning therapy applies sports-performance science to posture rehabilitation. Rather than correcting alignment passively, the clinician guides the patient to actively find and reproduce correct alignment using proprioceptive cues (the body’s sense of joint and muscle position), visual feedback, and progressive loading. Because the brain is actively learning the new pattern rather than having it imposed, the changes tend to last.


The most interesting work is in objective measurement. In patients with FHP, a combined program of cervical strengthening, thoracic mobilization, and proprioceptive training has been shown to reduce craniovertebral angle deviation (the most common radiographic measure of FHP severity) by a clinically meaningful amount over roughly eight weeks, with no passive bracing involved.
High-quality ultrasound imaging in neck-pain populations has documented changes in deep cervical flexor muscle size after targeted exercise. After 10 to 12 weeks of motor control training, muscles that were visibly atrophied at baseline showed measurable growth. Passive bracing does not produce that kind of structural change.
Bracing is still strongly supported in one specific area of spinal alignment: in adolescents with idiopathic scoliosis (a sideways spinal curve that first appears in the teen years), thoracolumbosacral orthosis (TLSO) bracing was proven in the BRAIST trial to slow curve progression in moderate curves when worn for the recommended hours per day. Adult posture braces are an entirely different category of product and should not be confused with the clinically proven bracing used for scoliosis.


If you have an existing spine diagnosis and are considering a posture brace, seek a clinical evaluation before using one.
These need specialist management, and posture rehabilitation, if appropriate, should follow rather than replace that care.
Most clinics do not have in-house objective diagnostic tools. NYDNRehab does. Clinicians use high-resolution dynamic ultrasonography to assess tissue quality and identify which muscles underperform during movement, so a rehabilitation plan can be built on objective findings. Computerized gait analysis evaluates posture during movement, not just in standing.
Treatment incorporates evidence-informed methods such as Dynamic Neuromuscular Stabilization (DNS), Stecco fascial manipulation, and ultrasound-guided techniques where indicated. Extracorporeal shockwave therapy (ESWT) can be used for soft-tissue conditions linked to chronic postural loading, such as thoracic trigger points and myofascial restrictions.
Assessment starts with the individual’s postural pattern, its functional consequences, and its likely cause, rather than with fitting a device. A wearable biofeedback sensor is not a substitute for a clinical plan, though it can accelerate one.


If you have neck or back symptoms or limited movement you think is posture-related, a tailored evaluation at NYDNRehab gives an objective picture of what is happening and a targeted plan to address it.
Request an appointment»

Our location: 11 West 25th Street 5th floor, New York, NY 10010
No. Passive posture braces are not muscle- or movement-retraining devices; they are positional reminders. Used without exercise and motor retraining, posture reverts once the brace comes off.
If a clinician prescribed one as part of a plan, follow their instructions. As a general rule, short periods of active movement training beat all-day wear, since constant use can reduce muscle recruitment and stall real improvement.
It can. FHP places the small muscles at the base of the skull (suboccipital muscles) under tension and can refer pain to the head, contributing to tension-type and cervicogenic headache (headache arising from the cervical spine), which is a recognized clinical entity with its own diagnostic criteria.
The marketing overlaps, but the mechanism differs. A wearable sensor (for example a vibrotactile feedback device) encourages active muscle involvement, while a passive brace provides no feedback. The evidence for vibrotactile feedback in healthy adults is more promising than for passive bracing.
The best-supported options include deep cervical flexor training (chin tucks, slow nodding against gravity), thoracic extension over a foam roller, scapular retraction and depression, hip flexor stretching, and diaphragmatic breathing drills. An individualized assessment matters, since the right combination depends on your specific postural pattern.
Yes. Where there is no fixed structural change in the cervical spine, most adults can achieve measurable improvement in head-neck alignment with consistent targeted exercise over 8 to 12 weeks. The realistic degree of improvement depends on severity, age, and any disc degeneration, and should be discussed with the clinician who assessed you.
Seek a professional assessment if posture comes with neurological symptoms (numbness, tingling, arm or leg weakness), if symptoms have not improved after six weeks of over-the-counter measures, or if any symptom persists beyond six weeks.
Dr. Lev Kalika is a world-recognized expert in musculoskeletal medicine. with 20+ years of clinical experience in diagnostic musculoskeletal ultrasonography, rehabilitative sports medicine and conservative orthopedics. In addition to operating his clinical practice in Manhattan, he regularly publishes peer-reviewed research on ultrasound-guided therapies and procedures. He serves as a peer reviewer for Springer Nature.
Dr. Kalika is an esteemed member of multiple professional organizations, including:

Below is a prime example of how ultrasound can take the guesswork out of diagnosis.

A bad physical therapy experience is one of the primary causes of unnecessary surgery

In this instance, an athlete was originally diagnosed with minor quadriceps muscle strain and was treated for four weeks, with unsatisfactory results. When he came to our clinic, the muscle was not healing, and the patients’ muscle tissue had already begun to atrophy.
Upon examination using MSUS, we discovered that he had a full muscle thickness tear that had been overlooked by his previous provider. To mitigate damage and promote healing, surgery should have been performed immediately after the injury occurred. Because of misdiagnosis and inappropriate treatment, the patient now has permanent damage that cannot be corrected.
The most important advantage of Ultrasound over MRI imaging is its ability to zero in on the symptomatic region and obtain imaging, with active participation and feedback from the patient. Using dynamic MSUS, we can see what happens when patients contract their muscles, something that cannot be done with MRI. From a diagnostic perspective, this interaction is invaluable.
Dynamic ultrasonography examination demonstrating
the full thickness tear and already occurring muscle atrophy
due to misdiagnosis and not referring the patient
to proper diagnostic workup
Demonstration of how very small muscle defect is made and revealed
to be a complete tear with muscle contraction
under diagnostic sonography (not possible with MRI)
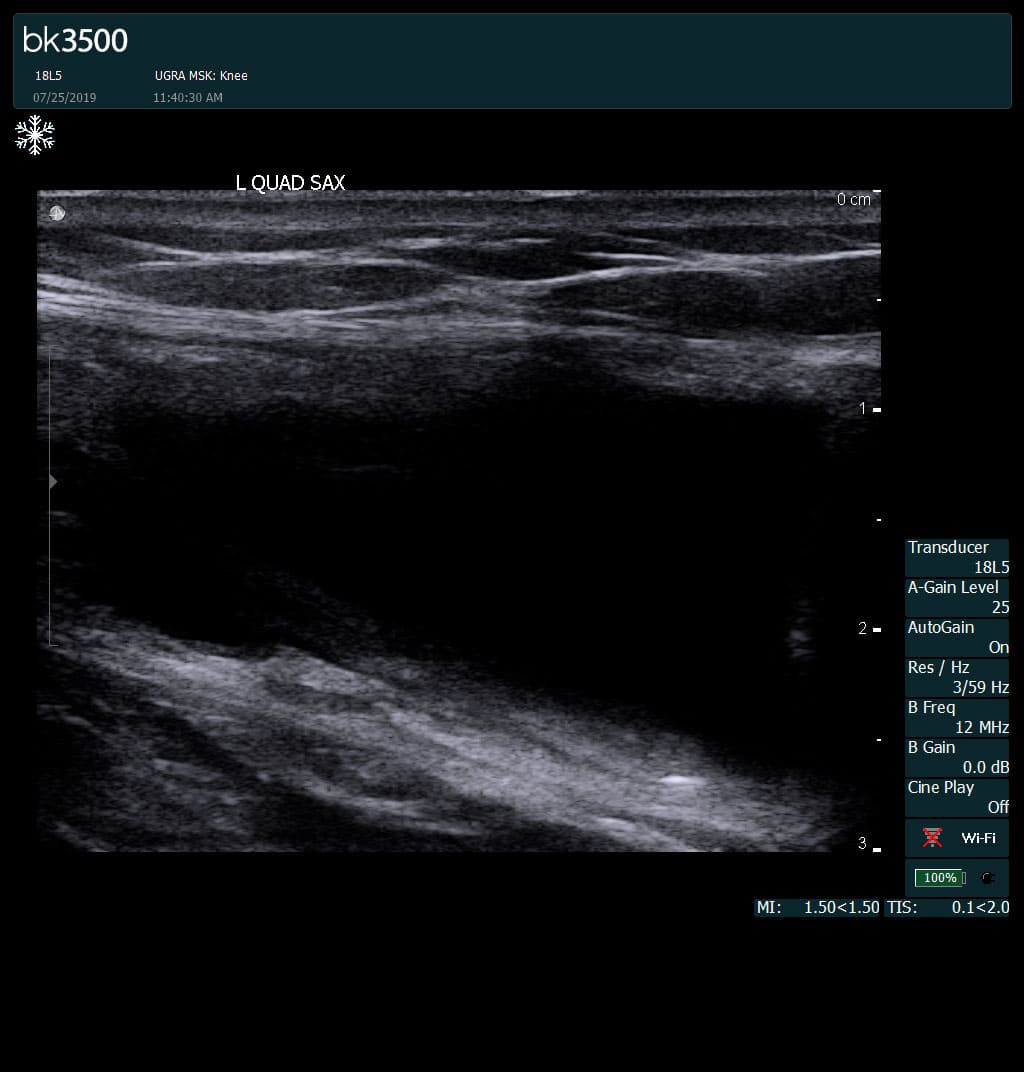
Complete tear of rectus femoris
with large hematoma (blood)
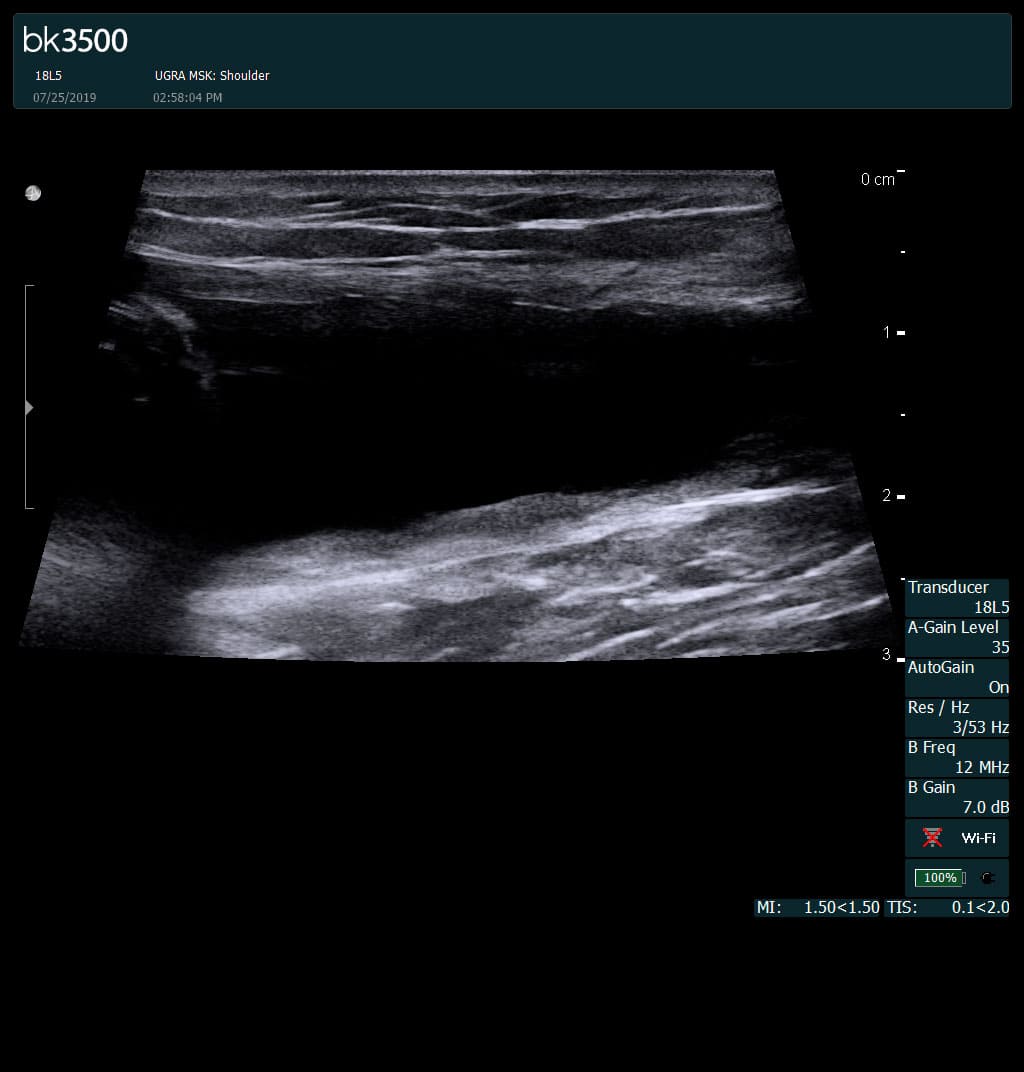
Separation of muscle ends due to tear elicited
on dynamic sonography examination


 Request Telehealth