August 25, 2026

About This Resource: This article was reviewed by the clinical team at NYDNRehab, a rehabilitation and physical therapy practice in New York City specializing in cervical spine dysfunction, postural rehabilitation, and chronic pain management. NYDNRehab uses advanced diagnostic and treatment approaches, including dynamic ultrasound imaging, cranio-cervical flexion testing, and individualized rehabilitation programs, to identify and address the root causes of musculoskeletal pain.

Introduction
When headaches recur with neck pain or stiffness, you’re not the only one. Cervicogenic headaches are often misdiagnosed and are highly responsive to specific rehabilitation when properly diagnosed. Our physical therapy team at NYDNRehab in New York City regularly assists patients in New York City to uncover the underlying cause of these headaches, and treat it using personalized cervical rehab programs.
A large number of people think that if they have recurring headaches, it must be a migraine headache or a tension-type headache, but a large percentage of people do have problems with their cervical spine. Education, exercise, and behavioral modification are a viable and evidence-based approach for improving cervical health by addressing poor posture habits, and are one of the most modifiable factors to influence cervical health.
A cervicogenic headache is a secondary headache, which occurs due to dysfunction in the upper cervical spine, that is the joints, muscles, nerves and soft tissue of the neck. The trigeminocervical complex (TCC) is a shared neurological pathway between the upper cervical nerve roots and the trigeminal nerve, and is felt in the head, forehead or around the eyes.
 Origin
 Location
 Neck pain
 Nausea
 Aggravated by neck movement
 Neurological symptoms
The Neuro-Anatomy of Referred Pain: The TCC is a neurological center where the sensory fibers of the cervical nerve roots C1, C2 and C3 meet the trigeminal nerve. If the upper neck joints or muscles are irritated, the brain will misinterpret the signals as being from the forehead, temples or behind the eye, so treatment of the neck is frequently the most effective.
1. My headaches start at the back of my neck or base of my skull
2. My headache is typically on one side and doesn’t move from side to side
3. Turning or tilting my head makes my headache worse
4. I spend 4+ hours a day at a desk, computer or phone
5. I have stiffness or limited range of motion in my neck which is obvious to others
6. My headaches are associated with a feeling of tightness in my shoulders or upper back
7. I have pain in my neck before or during my headaches
8. I have to move a lot to relieve my headaches


If you answered 5 or above and live in NYC, you may want to make an appointment for a cervical spine evaluation with NYDNRehab to get help diagnosing your cervicogenic headache with the advanced assessment tools they use.
Diagnosis should always be confirmed by a trained health care professional with clinical evaluation and imaging.
Cervical dysfunction is a common and often overlooked contributor to headache. Studies have shown that impaired performance of deep neck flexor muscles and impaired cranio-cervical flexion (the gentle nodding motion controlled by the deepest cervical muscles) is a cause of cervicogenic headaches. A weakness or abnormalities in the cervical facets (small paired joints between each vertebra) may lead to chronic referred head pain.
Forward head posture is the position in which the head moves forward compared to the shoulders, thus creating a high mechanical load on the cervical spine. As the head moves forward just one inch, the load on the spine greatly increases, placing stress on the joints, muscles and intervertebral discs.


Longus colli and longus capitis (deep muscles along the front of the cervical vertebrae) are important for providing segmental stability. The sternocleidomastoid (SCM) compensates when it is underactive, changing the biomechanics of the cervicoscapular complex and increasing the risk of joint irritation and referred pain. These effects are aggravated by prolonged sitting, which also causes thoracic kyphosis and anterior pelvic tilt. Neuromuscular retraining is necessary to correct posture, and not just “standing up straight.
Disclosure: NYDNRehab may prescribe postural support devices as part of an individual assessment and treatment plan, such as the PostureJac.
In addition to corrective exercises, postural support devices can be used to help alleviate the effects of cervical facet dysfunction.
There are three ways these devices operate:

Devices are tools, not standalone treatments. Do not wear them all the time, only during periods of active exercise. If symptoms do not decrease in frequency and/or postural awareness does not improve after 4-6 weeks of using the device and exercising, review your strategy with a qualified clinician.
Avoid starting without a health care professional’s advice if you have: cervical instability, recent whiplash or trauma, inflammatory arthritis of the cervical spine, osteoporosis, or progressive neurological symptoms.
Exercises are done in a sequence, one exercise builds up the tissues for the following exercise.
Exercise 1: The Release
Frequency: No more than 5 times a day, discontinue if numbness or dizziness occurs.
Relaxes the upper trapezius and sternocleidomastoid.
Exercise 2: Chin Tucks
2-3 series of 10-15 reps per day, hold for 5 seconds; stop if dizziness worsens.
Engages and tones the deep cervical flexors.
Exercise 3: Scapular Retractions
Perform 2-3 times per day, 10-15 reps each, 5 seconds hold, no shrugging.
Tones up the middle trapezius and rhomboids.
Exercise 4: Doorway Chest Stretch
3 repetitions per day, 20-30 seconds hold \ Stretch should be comfortable, not painful
Extends the shortened pectoral muscles
Exercise 5: Thoracic Extension over foam roller
The number of passes is 2–3 per day and support the head throughout.
Activates the thoracic spine and decreases cervical compensations.

What about the program not working? If after 6-8 weeks of following this program you have not seen any significant improvement, get a professional assessment. Clinicians at NYDNRehab leverage dynamic ultrasound imaging and cranio-cervical flexion testing to determine areas of impingement and modify treatment as needed.

The research is ongoing, and results are different for each person. These results are based on education and do not guarantee results.
Measurable improvements in endurance of the deep neck flexors have been shown in clinical studies where the use of the postural support device was combined with corrective exercise, compared with those who were not treated (Jull et al., 2002).
The severity of dysfunction, consistency of exercise, habits at work, fitness level, and whether the exercise is clinically directed or not, all influence the level of improvement. Patients often find that they start to improve gradually within 4 to 6 weeks of diligent effort. Individually tailored rehabilitation programs are created at NYDNRehab to reflect each patient’s baseline condition, lifestyle, and functional goals, to help establish realistic and meaningful rehabilitation milestones. No guarantees for any specific outcome for any individual.

Residents of New York City who are having any of the above should encourage them to seek immediate evaluation. Patients who have persistent, worsening, or complex headache presentations are eligible for a comprehensive cervical spine assessment at NYDNRehab.
Yes. The upper cervical spine is strained in FHP, and can irritate structures that refer to pain in the head. All factors are determined using a clinical evaluation.
Joint irritation, weakness of the deep flexor muscles of the neck, poor posture, previous neck injuries and prolonged static postures are all potential causes of referred head pain via common pathways between the cervical spine and the trigeminal nerve.
If there is a true cervicogenic component, targeted rehabilitation can help decrease the frequency and severity of headaches. Results are contingent on consistency and severity of dysfunction.
Changes are usually seen within 4-6 weeks. It takes several months of practice to become sustainable.
No. Braces create awareness, but they do not help to strengthen muscles. To get lasting benefits, one must be active in exercise.
Seek early professional evaluation if headaches are severe, worsening, neurological or do not improve after consistent care for several weeks.
Cervicogenic headaches can be a major cause of chronic headache that is often overlooked. Many people have a problem in the mechanics of the cervical spine due to bad postural habits, muscle imbalance, and the stresses of modern sedentary life. A comprehensive rehabilitation program that includes strengthening the deep neck flexor muscles, maintaining scapular stability, improving thoracic mobility and postural awareness provides a pathway and purpose for symptom reduction.
People who have headaches that do not go away or get worse should consult a healthcare professional for evaluation. The most important thing is to get an accurate diagnosis and a tailored rehabilitation plan, which will give you the best chance of making a long-term improvement.
Self-assessment tools and general exercises can be a good initial step, but can’t be used to determine if your headaches are cervicogenic and can’t design a treatment plan to meet your needs unless you have a qualified clinician.
NYDNRehab provides extensive cervical spine assessments in NYC, which include a postural assessment, cranio-cervical flexion testing, dynamic ultrasound imaging and individualised rehabilitation programming. Schedule Your Evaluation at NYDNRehab → Serving patients throughout New York City and the surrounding area.
The content of this article is for general educational information only and is not intended to be medical advice. Please always check with a trained health care provider before starting any exercise or rehabilitation program.
Request an appointment»

Our location: 11 West 25th Street 5th floor, New York, NY 10010

Verified Expert Profiles


Dr. Lev Kalika is a world-recognized expert in musculoskeletal medicine. with 20+ years of clinical experience in diagnostic musculoskeletal ultrasonography, rehabilitative sports medicine and conservative orthopedics. In addition to operating his clinical practice in Manhattan, he regularly publishes peer-reviewed research on ultrasound-guided therapies and procedures. He serves as a peer reviewer for Springer Nature.
Dr. Kalika is an esteemed member of multiple professional organizations, including:

Below is a prime example of how ultrasound can take the guesswork out of diagnosis.

A bad physical therapy experience is one of the primary causes of unnecessary surgery

In this instance, an athlete was originally diagnosed with minor quadriceps muscle strain and was treated for four weeks, with unsatisfactory results. When he came to our clinic, the muscle was not healing, and the patients’ muscle tissue had already begun to atrophy.
Upon examination using MSUS, we discovered that he had a full muscle thickness tear that had been overlooked by his previous provider. To mitigate damage and promote healing, surgery should have been performed immediately after the injury occurred. Because of misdiagnosis and inappropriate treatment, the patient now has permanent damage that cannot be corrected.
The most important advantage of Ultrasound over MRI imaging is its ability to zero in on the symptomatic region and obtain imaging, with active participation and feedback from the patient. Using dynamic MSUS, we can see what happens when patients contract their muscles, something that cannot be done with MRI. From a diagnostic perspective, this interaction is invaluable.
Dynamic ultrasonography examination demonstrating
the full thickness tear and already occurring muscle atrophy
due to misdiagnosis and not referring the patient
to proper diagnostic workup
Demonstration of how very small muscle defect is made and revealed
to be a complete tear with muscle contraction
under diagnostic sonography (not possible with MRI)
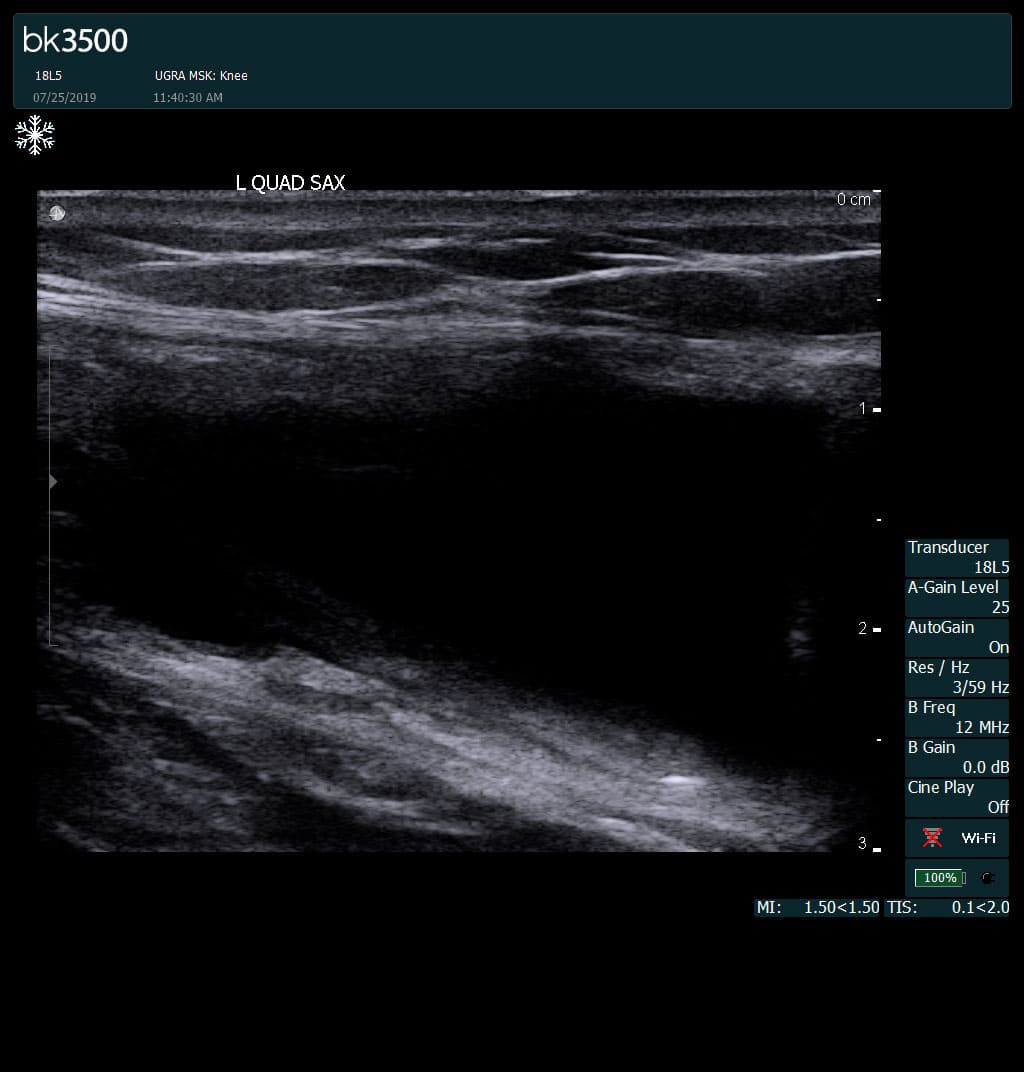
Complete tear of rectus femoris
with large hematoma (blood)
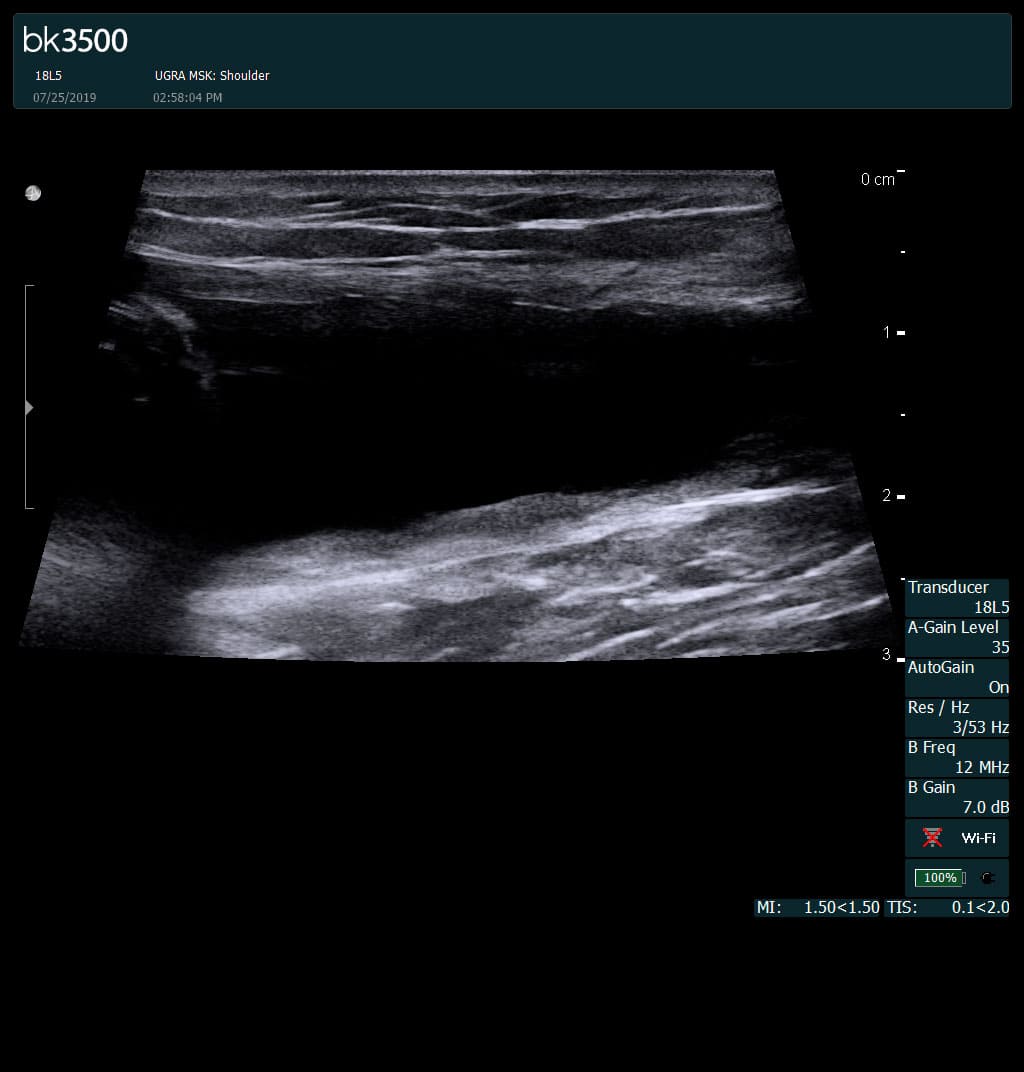
Separation of muscle ends due to tear elicited
on dynamic sonography examination


 Request Telehealth